
Download our evidence‑based Quadriceps Strain Rehab Protocol PDF, a step‑by‑step guide that outlines RICE, early mobilization, progressive strengthening, and return‑to‑sport criteria. Designed for athletes, it ensures safe, effective recovery and strength restoration. Follow the PDF for guidance. now!!!

Anatomy and Mechanics of the Quadriceps
The quadriceps femoris group comprises four muscles—rectus femoris, vastus lateralis, vastus medialis, and vastus intermedius—anchored to the patella via the patellar tendon. These muscles originate from the femur and pelvis, converge into a single tendon, and insert on the tibial tuberosity, enabling powerful knee extension and hip flexion. Their biomechanical role is crucial during activities such as walking, running, jumping, and squatting, where they absorb shock and generate force. The rectus femoris also assists in hip flexion, linking the upper and lower limbs. Understanding the quadriceps’ anatomy and mechanics is essential for designing targeted rehabilitation protocols that restore strength, flexibility, and functional performance while preventing re‑injury. The tendon’s attachment to the patella creates a lever system that amplifies muscular force, but also makes it vulnerable to overload, especially during high‑impact movements or rapid acceleration. Proper conditioning, progressive loading, and neuromuscular control are therefore key to maintaining joint stability and reducing strain risk.
The quadriceps tendon, a robust fibrous structure, connects the muscle group to the tibial tuberosity, transmitting forces during extension. Its tensile strength and elasticity allow rapid force production, yet repetitive loading can lead to micro‑tears, inflammation, or tendinopathy. Rehabilitation focuses on restoring tendon integrity, neuromuscular coordination, and joint proprioception to prevent recurrence.
Balanced loading recovery.!

Types of Quadriceps Injuries Covered
Quadriceps strain rehab protocol PDF addresses several injury categories that commonly afflict athletes. The guide distinguishes between muscle‑belle strains, tendon ruptures, and tendonitis, each requiring a tailored approach. Muscle‑belle strains range from mild micro‑tears to severe partial tears, involving the rectus femoris, vastus lateralis, or vastus medialis. Tendon ruptures, often acute and catastrophic, involve the patellar or quadriceps tendon and usually necessitate surgical repair followed by structured rehab. Tendonitis, a chronic overuse condition, presents as pain and swelling around the patella, requiring anti‑inflammatory strategies and gradual loading. Additionally, the PDF covers contusions, hematomas, and partial tendon tears, providing diagnostic criteria, imaging guidance, and specific therapeutic milestones. By categorizing injuries, the protocol ensures that each case receives evidence‑based, stage‑appropriate interventions, from RICE to advanced plyometrics, ultimately promoting safe return to sport. The document also highlights lesser‑known injuries such as isolated vastus medialis tendinopathy, rectus femoris avulsion, and combined muscle‑tendon injuries that may coexist. For each type, the PDF outlines assessment tools, including manual testing, ultrasound, and functional movement screens, to accurately identify the injury profile. Treatment pathways are mapped out with clear progression markers: initial pain control, controlled mobilization, progressive strengthening, neuromuscular re‑education, and sport‑specific drills. The protocol emphasizes individualized load management, ensuring that athletes do not exceed safe thresholds during each phase. Clinicians can also use the protocol to monitor progress via patient‑reported outcome measures and objective strength testing, ensuring that recovery milestones are met before advancing to high‑intensity activities. Ultimately, the PDF serves as a tool for physical therapists, athletic trainers, and sports medicine physicians to deliver care across all quadriceps injury types.

Assessment and Diagnosis
Quadriceps strain rehab protocol PDF outlines a systematic assessment framework that integrates history, physical examination, and imaging to accurately classify injury severity. Initial history captures mechanism (sudden eccentric load vs. repetitive micro‑trauma), onset of pain, swelling, and functional limitations; Physical exam focuses on inspection for bruising or deformity, palpation of the rectus femoris, vastus lateralis, and vastus medialis for tenderness, and testing of active and passive knee extension strength. The protocol recommends the “Quadriceps Strength Test” (isometric contraction against resistance) and the “Patellar Apprehension Test” to detect tendon instability. Range of motion is measured with a goniometer; a loss of >10° in extension flags a possible tendon tear. Functional tests such as single‑leg squat and hop endurance are used to gauge neuromuscular control. Imaging is reserved for equivocal cases: ultrasound or MRI confirms partial tendon rupture, full‑thickness tear, or chronic tendinopathy. The PDF provides a decision tree: mild strain (Grade I) requires RICE and early mobilization; moderate strain (Grade II) needs controlled loading; severe strain (Grade III) mandates surgical consultation. Throughout, the protocol emphasizes documentation of pain scores (VAS) and strength ratios (quadriceps to hamstring) to monitor progress and guide progression to the next rehabilitation phase. Clinicians should also consider factors such as activity level and previous injury history to tailor the comprehensive rehabilitation plan.
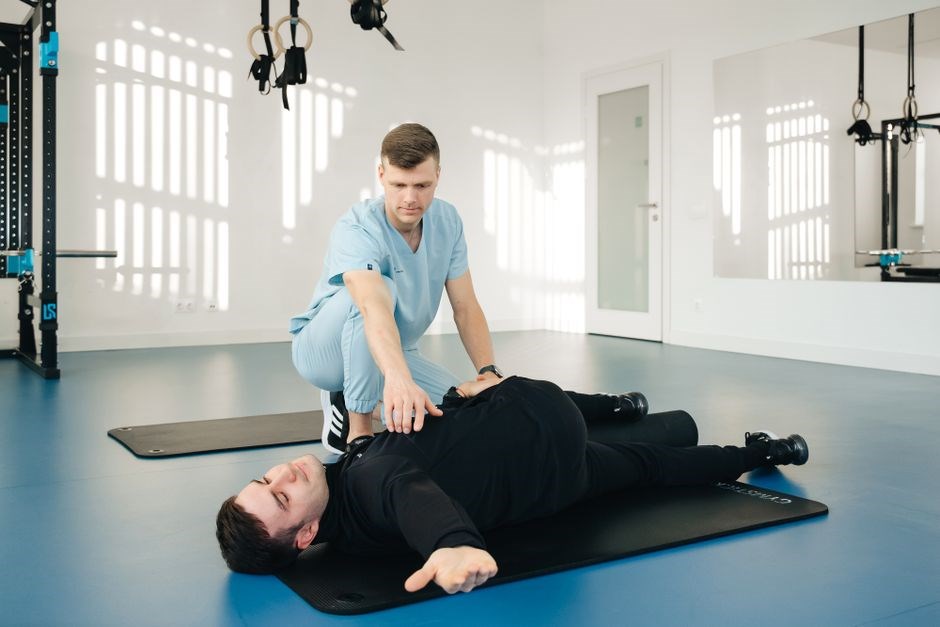
Rehabilitation Protocol Overview (PDF Guide)
The PDF guide presents a phased approach: Phase 1 RICE, Phase 2 early mobilization, Phase 3 progressive strengthening, Phase 4 sport return. Each phase lists specific exercises, progression criteria, and safety checkpoints to ensure a structured, evidence‑based recoveryFollow the PDF for detailed progression
Phase 1: Initial Management (RICE)
Phase 1 focuses on immediate injury control using the classic RICE protocol: Rest, Ice, Compression, and Elevation. Rest limits further mechanical stress on the quadriceps muscle belly, while ice reduces inflammation and numbs nociceptors, decreasing pain. Compression with a snug elastic bandage or wrap helps limit edema and provides proprioceptive feedback. Elevation above heart level promotes venous return, reducing swelling. Apply ice for 15–20 minutes every 2–3 hours during the first 48 hours. Use a compression wrap that exerts 20–30 mmHg pressure, ensuring it is not so tight as to impede circulation. Elevate the leg on pillows or a reclined chair so the knee is slightly bent, keeping the limb above the level of the heart. Throughout this phase, avoid weight‑bearing activities and high‑impact movements. Gentle passive range‑of‑motion exercises can be introduced once pain subsides, but avoid active quadriceps contractions. The goal is to control pain, swelling, and prevent further tissue damage, setting the stage for safe early mobilization in Phase 2. Follow the PDF guide for precise timing and technique details to optimize recovery. In addition, monitor for signs of excessive swelling, bruising, or neurovascular compromise; if these occur, reassess the compression level and consult a clinician. Maintaining proper posture during rest, avoiding prolonged sitting, and using a supportive brace can aid comfort. Consistent adherence to RICE principles during the first 72 hours maximizes tissue healing and reduces the risk of chronic dysfunction. Daily pain scores help tailor RICE intensity. Checks prevent complications. Use a firm wrap to avoid moisture buildup. Maintain a supportive pillow under the knee. Keep.
Phase 2: Early Mobilization and Strengthening
After the acute phase, Phase 2 introduces controlled movement and low‑load strengthening to restore range of motion and begin rebuilding quadriceps integrity.

Begin with gentle, pain‑free active‑assisted knee flexion and extension, progressing to closed‑chain exercises such as mini‑squats and wall sits.
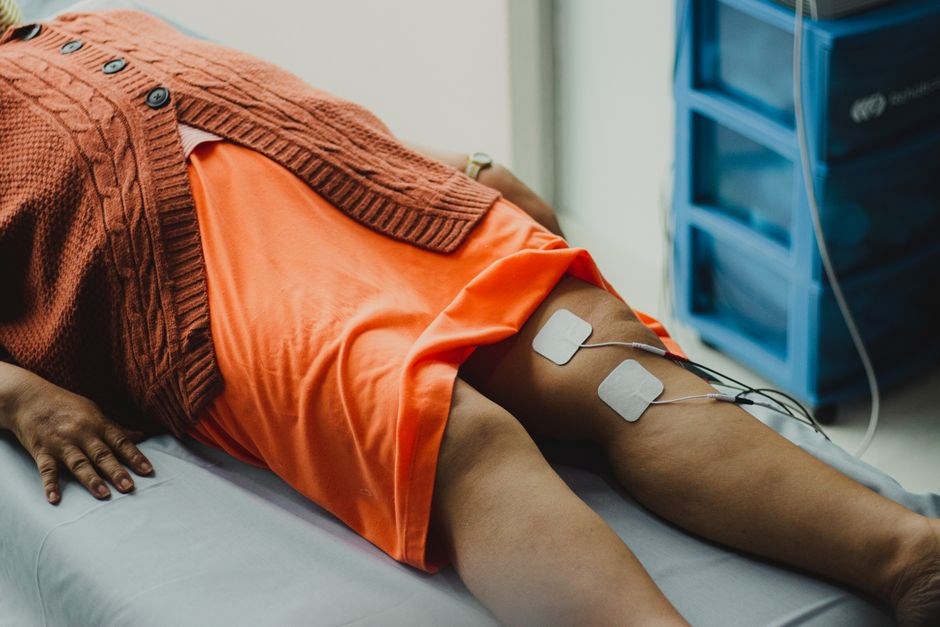
Use a light resistance band around the thighs for glute activation and to provide a gentle load on the quadriceps.
Maintain a 90° knee flexion angle during wall sits, holding for 10–15 seconds, and perform 3 sets of 10–12 repetitions.
Incorporate isometric quadriceps contractions by pressing the heel into the floor while keeping the knee bent at 30°, holding for 5 seconds, and repeating 15 times.
Progress to single‑leg balance on a stable surface, adding a light dumbbell held at the wrist to increase load gradually.

Emphasize proper form: keep the knee aligned over the toes, avoid valgus collapse, and keep the pelvis neutral.
Monitor pain; if it exceeds 3 on a 0–10 scale, reduce load or pause.
Continue daily stretching of the quadriceps and hamstrings to maintain flexibility.
The goal is to re‑educate the muscle, improve neuromuscular control, and prepare for more demanding dynamic tasks in Phase 3.
The PDF provides progression charts, cue sheets, and safety checklists to guide clinicians and patients through this critically stage!ly.
Adherence frequency—three sessions per week—ensuresand progression asyptom diary aids tailoringly.

Phase 3: Advanced Strengthening and Plyometrics
Phase 3 elevates load and introduces plyometric drills to restore power and dynamic stability. Begin with gentle, pain‑free active‑assisted knee flexion and extension, progressing to closed‑chain exercises such as mini‑squats and wall sits. Use a light resistance band around the thighs for glute activation and to provide a gentle load on the quadriceps. Maintain a 90° knee flexion angle during wall sits, holding for 10–15 seconds, and perform 3 sets of 10–12 repetitions. Incorporate isometric quadriceps contractions by pressing the heel into the floor while keeping the knee bent at 30°, holding for 5 seconds, and repeating 15 times. Progress to single‑leg balance on a stable surface, adding a light dumbbell held at the wrist to increase load gradually. Emphasize proper form: keep the knee aligned over the toes, avoid valgus collapse, and keep the pelvis neutral. Monitor pain; if it exceeds 3 on a 0–10 scale, reduce load or pause. Continue daily stretching of the quadriceps and hamstrings to maintain flexibility. The goal is to re‑educate the muscle, improve neuromuscular control, and prepare for more demanding dynamic tasks in Phase 3. The PDF provides progression charts, cue sheets, and safety guidelines to guide clinicians and patients through this critical stage.
Throughout Phase 3, clinicians should document subjective pain levels, objective strength metrics, and functional test outcomes. A structured progression chart assists in determining when to advance load or introduce higher‑impact drills. Adherence to a graded return‑to‑sport protocol ensures athletes regain confidence and performance while minimizing re‑injury risk. Stay!!
Phase 4: Return to Sport Criteria
Phase 4 confirms sport readiness. Clinicians evaluate pain‑free drills quadriceps strength ≥90 % of the contralateral limb, and full ROM. Functional tests—single‑leg hop, vertical jump, agility ladder—must show symmetry force. Neuromuscular control is checked with balance proprioception drills, ensuring stability. Sport‑specific drills (cutting, pivoting, sprint starts) are added after lower‑level tests succeed. A graded return schedule—4–6 weeks post‑injury—monitors pain, swelling, performance. Documentation of milestones, strength functional scores guides decision‑making. Clearance is granted only when the athlete meets all criteria, has no pain during sport‑specific activities, demonstrates confidence. Psychological readiness is assessed with the ACL‑RSI score, confirming acceptable confidence. The protocol recommends a final “pre‑return” assessment, where the athlete performs contact drill under supervision, confirming no pain. Coaches and therapists monitor load progression using GPS heart‑rate data to keep intensity within limits. The PDF includes a checklist timeline template to guide clinicians through milestones, ensuring consistency across sports. Clinicians verify sport‑specific movements at 70–80 % of maximal effort and restored proprioceptive thresholds within 10 % of baseline. Final clearance is granted collaboratively by the medical team, physiotherapist, coaching staff, ensuring stakeholder agreement. This multi‑disciplinary approach aligns with best practices, reducing re‑injury risk and enhancing long‑term performance!

Key Strengthening Exercises
Key strengthening exercises include quadriceps isometric holds, progressive squat variations (bodyweight, goblet, split), and resistance‑band drills (leg extensions, clamshells). These target muscle belly, improve joint stability, and accelerate functional recovery. Add plyometric drills for power, speed fast.
Quadriceps Isometric Exercises
Isometric contractions are the cornerstone of early quadriceps rehabilitation, allowing safe activation of the muscle belly without joint movement. The protocol begins with seated quad sets: sit with the knee fully extended, tighten the quadriceps, hold for 5–10 seconds, and release. Do 3–4 sets of 10–15 repetitions, resting 30–60 seconds between sets. Progress to wall sits, maintaining a 90‑degree knee angle, holding for 20–30 seconds, and repeating 3–4 times. For increased load, add a weighted vest or ankle weights, ensuring the knee remains in a neutral position to avoid undue patellar tracking. Next, incorporate the straight‑leg raise: lying supine, lift the affected leg to a 45‑degree angle, hold the contraction for 5 seconds, and lower slowly. Repeat 3–4 sets of 12–15 reps; Finally, perform the single‑leg isometric hold: standing, support the non‑injured leg on a stable surface, and press the heel of the injured leg into the floor, maintaining the knee at 30–45 degrees. Hold 10–15 seconds per set. Increase hold duration resistance as pain subsides, aiming for 30–45 seconds per set.
Throughout the isometric phase, focus on knee alignment to avoid valgus or varus stress. A therapist may use a mirror or video feedback to ensure the patella tracks centrally. If pain spikes, reduce hold time or add a light resistance band around the ankle to shift load. Combined with load increments, typically yields a 70–80% return to pre‑injury performance within 6–8 weeks, provided adherence to the protocol and avoidance of compensatory movements.!!
Progressive Squat Variations
Start with wall‑squat progression: stand 30 cm from a wall, slide down until the knees are at a 90‑degree angle, hold for 5 seconds, then slowly rise. Perform 3 sets of 10 reps, resting 60 seconds between sets. Once tolerated, add a light dumbbell held at the chest to increase load. Next, transition to a half‑squat: feet shoulder‑width apart, toes slightly angled out, descend until the thighs are parallel to the floor, pause for 2 seconds, and return upright. Aim for 3 sets of 8–10 reps, with a 45‑second rest interval. Progress to a full squat by extending the hips and knees fully, ensuring the knees track over the toes and the back remains neutral. Hold the bottom position for 3 seconds. Then rise. Complete 3 sets of 6–8 reps, resting 60 seconds. For advanced athletes, incorporate a pause squat: after descending to the bottom, pause for 5 seconds before ascending, which enhances eccentric control. Perform 3 sets of 5 reps. Finally, add a jump squat to re‑introduce plyometric loading: from a half‑squat position, explode upward with knees bent. Do 3 sets of 6 reps, resting 90 seconds. Throughout, monitor knee alignment, hip stability, and pain tolerance. Gradual progression in depth, load, and pause duration promotes safe quadriceps re‑strengthening and functional recovery. In addition, integrate light resistance bands during the squat to increase eccentric demand without joint loading. Use a band looped around the thighs, performing a controlled descent while maintaining knee alignment. Gradually increase band tension as strength improves, ensuring the patella tracks centrally. This technique enhances proprioception and muscular endurance, preparing the quad for sport‑specific demands. Keep form strict. Maintain proper posture. Stay consistent.!!
Resistance Band Exercises
In the quadriceps strain rehab protocol PDF, resistance band work is a cornerstone for restoring strength while protecting the healing tissue. Begin with a low‑resistance loop band, securing it around the thighs just above the knees. Perform a standing quad contraction: lift the heel toward the glutes, hold for 3 seconds, and slowly lower. Complete 3 sets of 12 reps, resting 30 seconds between sets. Progress by adding a slight external rotation of the hips during the contraction to engage the vastus medialis. Next, use a mid‑resistance band for seated knee extensions: sit on a chair, loop the band around the ankles, and extend the knee fully, pausing at the top for 2 seconds. Do 3 sets of 10 reps, with a 45‑second rest interval. For functional loading, incorporate a standing lateral band walk: place the band just above the knees, step sideways 10 steps, then return. This targets hip abductors and quad stabilizers. Perform 3 sets of 8 steps each direction. Finally, integrate a single‑leg band squat: loop the band around the thighs, stand on one leg, and squat to a 90‑degree angle, holding the bottom for 3 seconds. Repeat 3 sets of 6 reps per leg, resting 60 seconds. Throughout, maintain proper knee alignment, avoid valgus collapse, and monitor pain. Gradual load increases and controlled tempo are key to a safe, effective quadriceps recovery. The band exercises should be performed daily, with progression guided by pain thresholds and functional milestones. Consistency, proper technique, and gradual load escalation ensure the quadriceps regains full strength and resilience, preparing the athlete for a safe return to sport.!!